
The clinical landscape for peptide and nanobody conjugates is expanding rapidly. In this article we look at the clinical landscape with respect to therapeutic disease, mechanism of action, targets, and geographic trends.
A conference presentation at Protein & Antibody Engineering Summit (PEGS) 2026, based on Pharmaprojects data and pipeline analysis by Laurie Withington, Associate Director of Clinical Trials Intelligence, Citeline
The next wave of targeted therapeutics is being built on smaller scaffolds. At PEGS 2026, a Citeline analysis of the global drug pipeline counted 106 peptide and nanobody drug conjugates in active development — a field still concentrated in its earliest stages but already producing approved products and a cluster of late-stage candidates expected to reach regulators within the year.
The clinical landscape for peptide and nanobody conjugates is expanding rapidly. Peptide drug conjugates (PDCs) are advancing mainly through oncology pipelines and nanobody drug conjugates (NDCs) are emerging as next‑generation precision biologics, with the majority being earlier stage. Here we look at the clinical landscape with respect to therapeutic disease, mechanism of action, targets, and geographic trends.
PDCs are in a growth phase due to their many advantages. These include superior tumor penetration, low immunogenicity, reduction of off-target toxicity, improved pharmacokinetics (PK), a higher drug-to-carrier ratio, synthetic flexibility and scalability, and theranostic potential. Also, they are easier and less expensive to manufacture. On the flip side, PDCs present several challenges such as immunogenicity issues and premature payload release.
Likewise, NDCs hold much promise due to numerous advantages, including strong tissue penetration, low-cost industrial production, a variety of conjugation strategies, quicker systemic clearance, and improved drug-to-antibody ratio (DAR). NDC challenges include potentially costly and difficult site-specific conjugation techniques, especially at large scale, and lack of well-established pathways to approval.
Challenges impacting both PDCs and NDCs include poor PK profile, a short half-life, and low oral bioavailability.
Drawing on Pharmaprojects data current to January 2026, the analysis found roughly 63% of the 106 conjugates sitting in preclinical development and about 20% in Phase I. Only some 13% have advanced to Phase II or III, with a further 3% at pre-registration. Three peptide-drug conjugates have reached approval: Lutathera, a peptide-isotope conjugate cleared for somatostatin receptor-positive gastroenteropancreatic neuroendocrine tumors (GEP-NETs); Pepaxto, an antiangiogenic peptide-melphalan conjugate for multiple myeloma (withdrawn from the US market in 2024); and Mepact, a peptide-liposomal conjugate approved outside the US for osteosarcoma.
China and the United States together account for about 80% of all development activity, with the UK and Belgium contributing a further 19–22% of programs. PDCs make up the bulk of the field at 82 drugs — led by China, then the US and UK — while NDCs remain a smaller but distinct group of 24 candidates, where China leads ahead of Belgium and the US. In the clinic the picture shifts: The US holds the largest share of Phase I-to-approved PDCs, reflecting a US lead in advancing these molecules out of preclinical research.
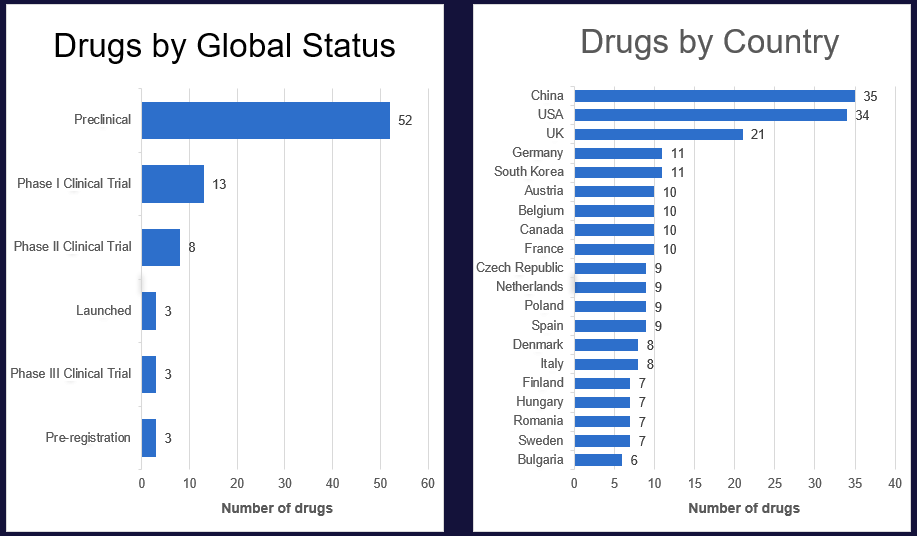
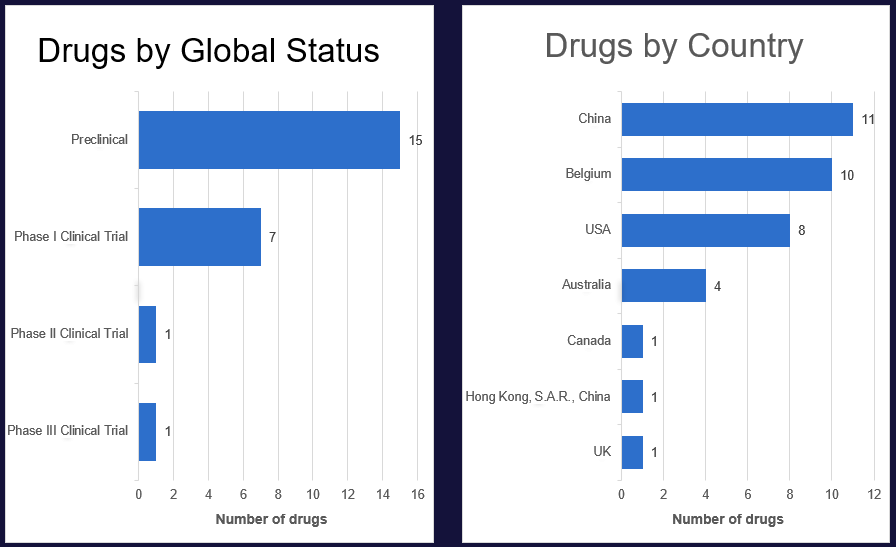
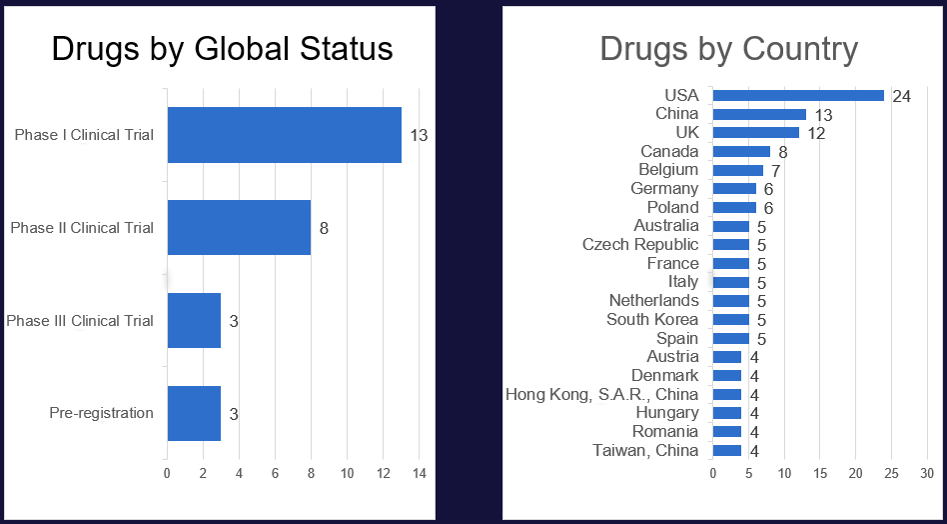
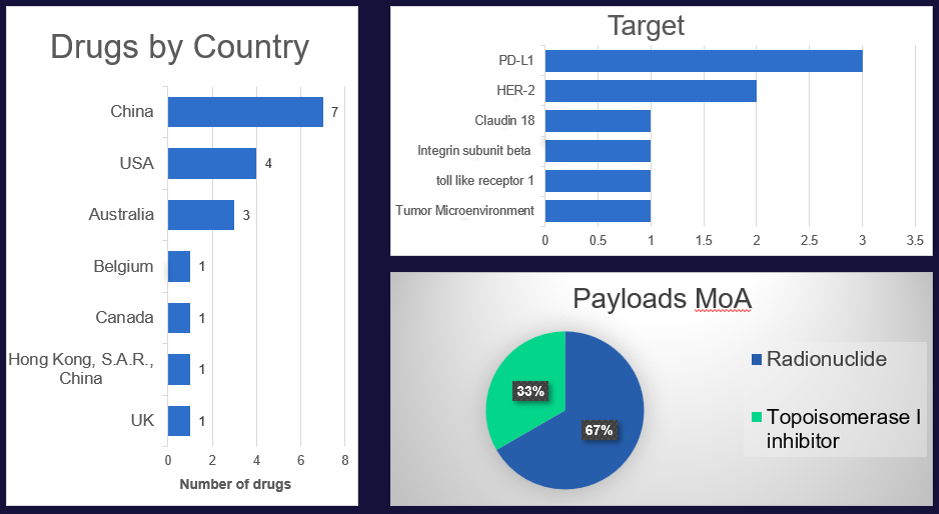
Across both modalities, oncology remains the overwhelming therapeutic focus, followed by obesity, osteoarthritis, type II diabetes and cardiovascular disease. Among the 27 PDCs in Phase I through pre-registration, three-quarters are antagonist conjugates and one-quarter agonists, spanning payloads from radionuclides and tubulin inhibitors to monomethyl auristatin E (MMAE) and topoisomerase inhibitors. Leading cancer targets include neuroendocrine tumors and breast/prostate cancers, while the top non-cancer indications are type II diabetes and obesity, growth disorders, and dry eye disease. NDCs lean heavily on radionuclide payloads, with most candidates aimed at PD-L1 and HER2.
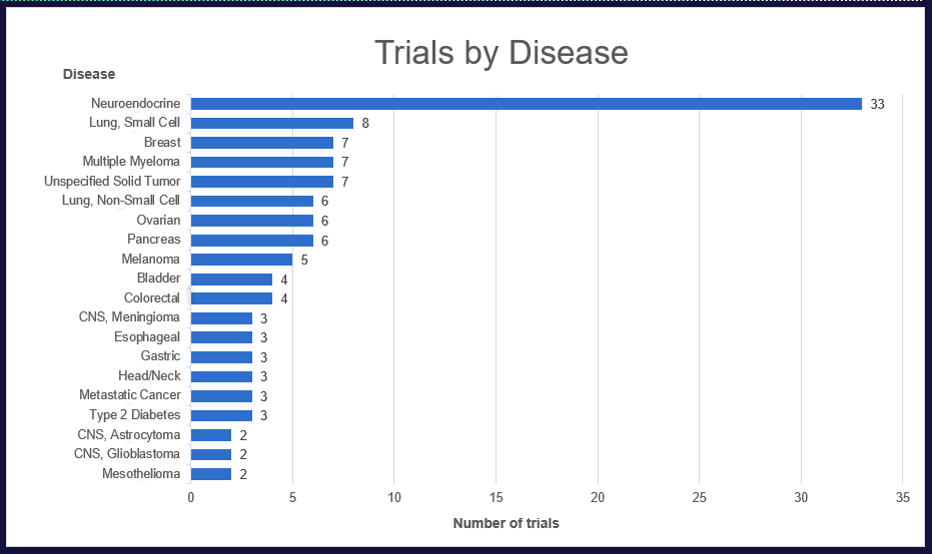
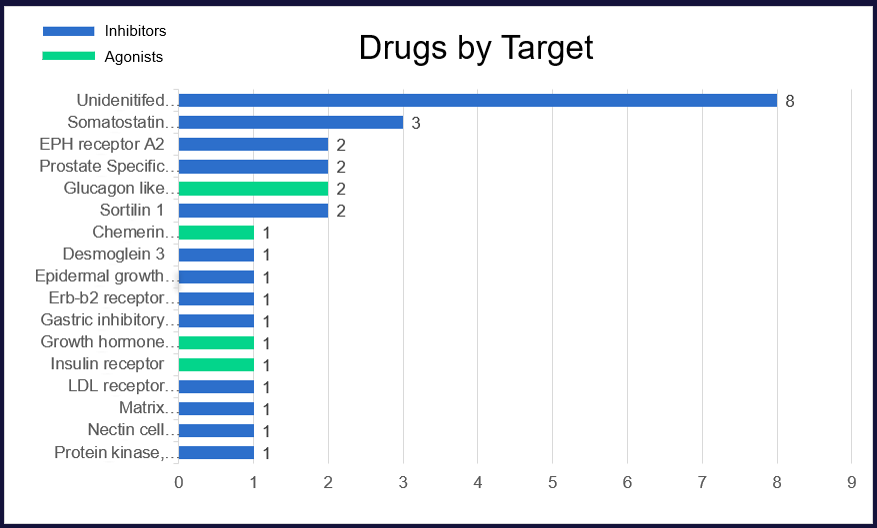
Seven unapproved PDCs are furthest along, supported by 18 pivotal trials. Three are at pre-registration with approvals anticipated this year: efpeglenatide (Hanmi Pharmaceutical), an exendin-4-IgG4 Fc conjugate for type II diabetes and obesity, with an obesity approval expected in 2026; 177Lu-edotreotide (ITM Isotope Technologies Munich SE) for GEP-NETs, carrying a PDUFA date of August 2026; and efsitora (Eli Lilly), a single-chain insulin variant for type II diabetes, also expected in 2026. Behind them sit ANG1005 and bel-sar in Phase III, urcosimod in Phase II, and faridoxorubicin in Phase I.
Learn more about Pharmaprojects, the gold standard in pharma industry intelligence.


